The monofilament test: what a failed foot sensation test means and what to do next
A 10-gram monofilament pressed on the sole shows whether your foot can feel an injury. A failed test means loss of protective sensation, and fixing deformity or a trapped nerve can lower the risk that follows.

By Dr. Efe Ozturk · 6 min read
Medically reviewed by Dr. Efe Ozturk · Last reviewed
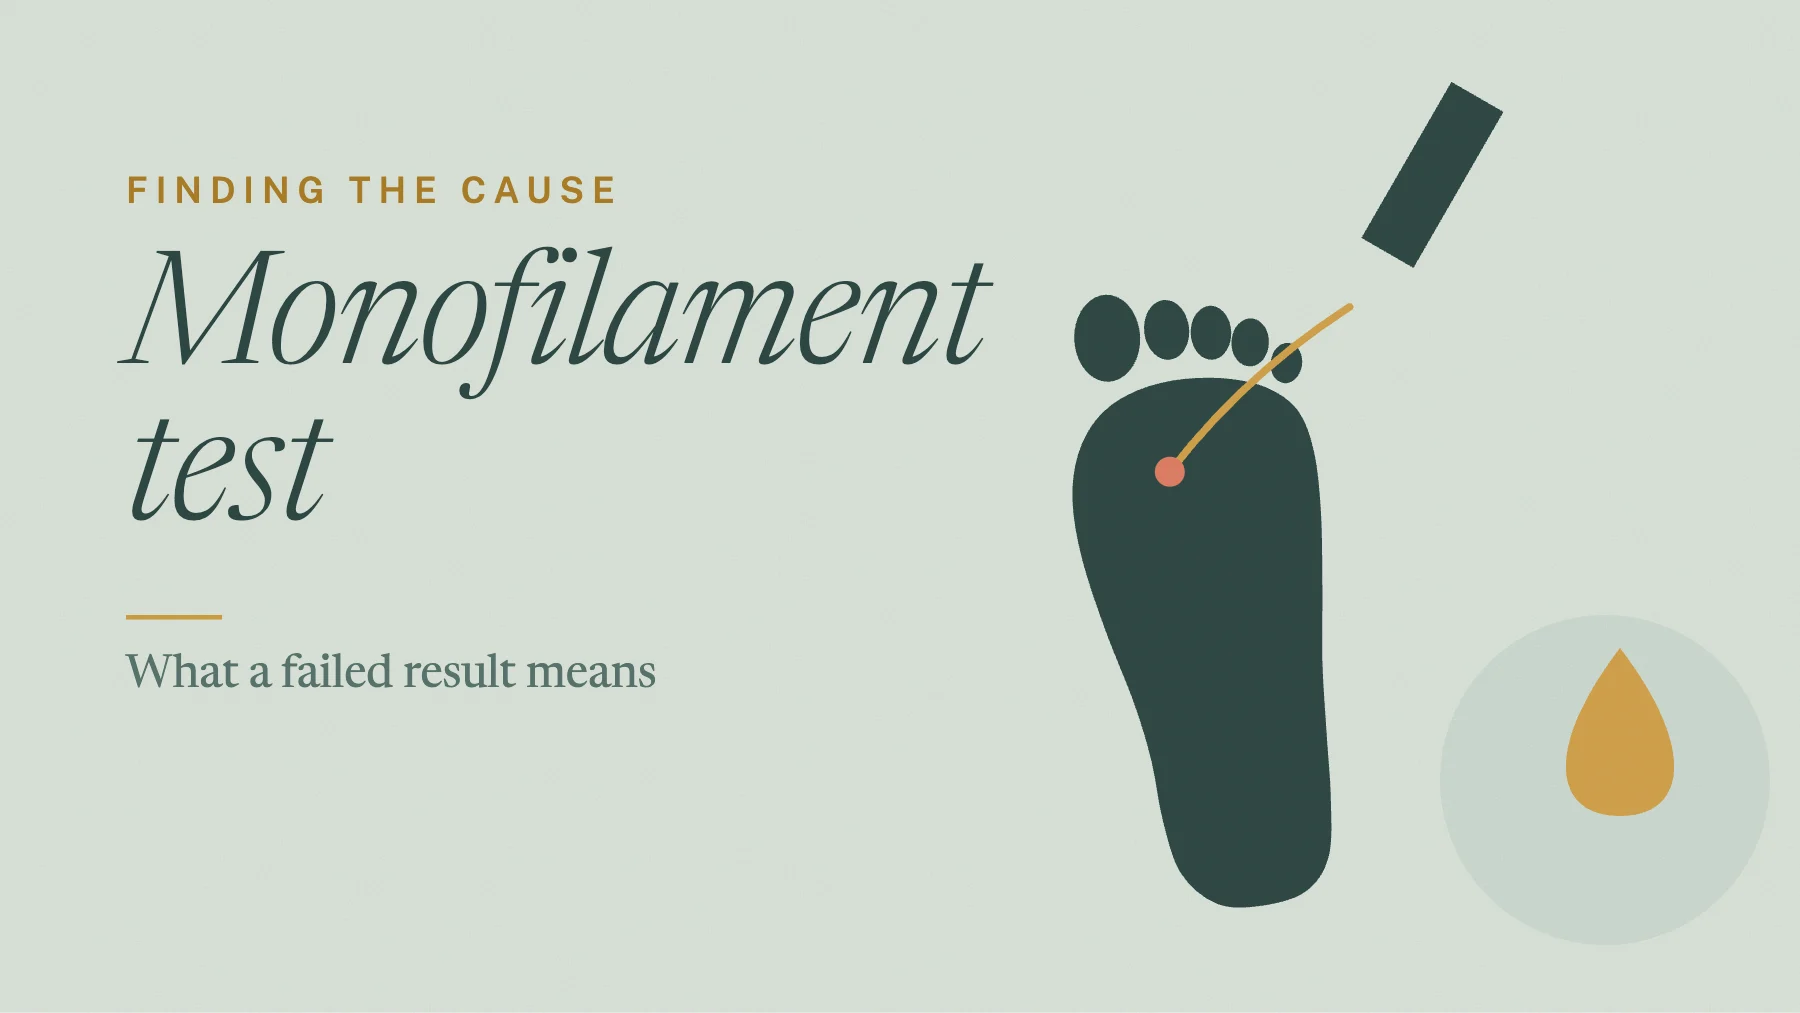
November is National Diabetes Month, and World Diabetes Day falls on November 14.[6,7] It is a good time to ask about the monofilament test, a quick foot check with a big job: spotting feet that can’t feel an injury. Here is what the test is, what a failed result means, and what a Foot and Ankle Surgeon can do next.
What is the monofilament test?
The tool is a nylon thread on a handle. It is built to buckle when it presses with 10 grams of force. It was first used to find lost feeling in leprosy.[1]
Here is how it is done:[1]
- You feel it first on your arm, so you know what to expect.
- You close your eyes.
- The thread is pressed straight against the skin until it bends, held about one second, then lifted.
- You say “yes” when you feel it and point to where.
- Calluses are skipped, because thick skin blocks the feel.
Monofilament test sites: where on the foot?
A task force of the American Diabetes Association recommends four spots on the sole of each foot: under the tip of the big toe, and three spots on the ball of the foot, under the first, third and fifth metatarsal heads (the knobby ends of the long foot bones).[1]
The monofilament is one part of a full foot exam. That exam also looks at the skin and foot shape, checks pulses, and adds at least one more feeling test, such as vibration with a tuning fork, pinprick or temperature.[2]
Monofilament test scoring: what does a failed test mean?
The task force says one or more abnormal tests suggest LOPS, and two normal tests with no abnormal ones rule it out.[1] The 2026 ADA Standards say a missed monofilament plus one other abnormal test confirms LOPS.[2]
LOPS is not a score of how bad your neuropathy feels. It means you could step on a tack or wear a blister and not notice. That is why it matters. In pooled data from more than 16,000 people with diabetes, not feeling the monofilament roughly tripled the odds of a foot ulcer. A past ulcer raised them even more.[8]
Your result also sets how often your feet should be checked:[2]
- No LOPS and good circulation: once a year.
- LOPS or poor circulation: every 6 to 12 months.
- Two of these: LOPS, poor circulation, a foot deformity: every 3 to 6 months.
- LOPS or poor circulation plus a past ulcer, an amputation or kidney failure: every 1 to 3 months.
Is the monofilament test accurate for neuropathy?
It is better at ruling in than ruling out. In a JAMA review, an abnormal monofilament made large-fiber neuropathy far more likely.[9] But compared with nerve conduction studies, the test caught only 53% of people with diabetic neuropathy.[10] A passed test does not prove your nerves are healthy, and experts advise against using it alone to diagnose neuropathy.[11]
When the pattern is unusual, nerve conduction studies and EMG can help. We arrange those with another specialist and go over the results with you. Learn more about peripheral neuropathy.
A failed monofilament test: where surgery fits
A failed test means the foot can’t warn you. The surgeon’s job is to remove what would injure it, and sometimes to free a nerve.
Correcting deformity to prevent ulcers. Dr. Efe Ozturk, a double board certified Foot and Ankle Surgeon and podiatrist, looks for the bony bumps, clawed toes and tight tendons that put pressure on a numb foot. When special shoes can’t manage a deformity, or ulcers keep coming back, the ADA says to consider reconstructive surgery by a surgeon experienced with the diabetic foot.[2]
- Achilles lengthening. In 64 people with diabetes and an ulcer under the forefoot, all ulcers in the lengthening group healed. At two years, ulcers had come back in 38% of them, versus 81% with a cast alone. The authors recommend it when a tight calf keeps the ankle from bending up more than 5 degrees.[3]
- Flexor tenotomy. For a flexible hammertoe, the toe tendon can be released through a tiny cut. In five studies of 163 people with diabetic toe ulcers, healing rates were at least 92% within about two months, and 0% to 18% of ulcers came back.[12] The international foot guideline suggests considering it for a flexible hammertoe with a pre-ulcer.[13]
Our limb salvage team explains ulcers from foot deformity (external site).
Finding a trapped nerve. Neuropathy usually affects both feet evenly.[14] Numbness that is much worse in one foot does not fit the usual pattern and needs a closer look.[15] One cause is a tibial nerve trapped behind the inner ankle (tarsal tunnel syndrome). A sign of this trapped nerve, a tingle when it is tapped, was found in 44.9% of people with diabetes, versus 26.5% of healthy people without diabetes.[4] People with diabetes and tarsal tunnel syndrome in both feet developed ulcers about twice as often.[16]
Releasing a trapped tibial nerve can help. In 62 people with tarsal tunnel syndrome from a range of causes (some had diabetes), average foot scores rose from 61 (in those measured) to 80 out of 100 after tarsal tunnel release.[5] We do not offer decompression as a treatment for neuropathy itself. When you also have clear signs of a trapped nerve, we assess that nerve on its own merits. See nerve decompression surgery for diabetic neuropathy.
What else happens after a failed test?
- Your feet get checked at every visit.[2]
- You learn daily foot care. Our main practice shows how in the diabetes daily foot check (external site).
- Shoes. Therapeutic footwear is advised for people at high risk, including those with deformities.[2]
What are the limits?
The monofilament misses about half of neuropathy, so it is a screening tool, not a full nerve test.[10] The tenotomy studies were small case series without control groups.[12] The international foot guideline suggests not using nerve decompression to prevent foot ulcers.[13]
Common questions
How is the monofilament test scored?
Each spot is either felt or not felt. An abnormal monofilament result plus one other abnormal feeling test confirms LOPS.[1,2]
What are the monofilament test sites?
The task force recommends four spots per foot: the tip of the big toe and the ball of the foot under the first, third and fifth metatarsal heads.[1]
How often should people with diabetes have a monofilament test?
At least once a year, and more often once feeling is lost.[2] Read diabetic neuropathy: when to see a nerve specialist.
When to see a specialist
Book an evaluation if you failed a monofilament test, haven’t had a foot exam this year, notice a change in your foot’s shape, or have numbness that is worse in one foot. We see patients in Lyndhurst, Paramus and Millburn. Please call our office at 908-215-5953 to inquire about your insurance.
About the author
Dr. Efe Ozturk
Foot and Ankle Surgeon. Dr. Ozturk is double board certified, as a Diplomate of the American Board of Podiatric Medicine (DABPM) and a Fellow of the Academy of Physicians in Wound Healing (FAPWH), and is a Fellow of the American Society of Podiatric Surgeons (FASPS) and the American Society of Podiatric Medicine (FASPM). He leads the Lower Extremity Nerve Institute, a specialty practice of Ozturk Foot & Ankle, and sees patients in Lyndhurst, Paramus and Millburn, New Jersey.
References
- 1.Boulton AJ, Armstrong DG, Albert SF, et al. Comprehensive foot examination and risk assessment: a report of the task force of the foot care interest group of the American Diabetes Association, with endorsement by the American Association of Clinical Endocrinologists. Diabetes Care. 2008;31(8):1679-1685. PubMed 18663232 (external site)
- 2.American Diabetes Association Professional Practice Committee for Diabetes. 12. Retinopathy, neuropathy, and foot care: Standards of Care in Diabetes-2026. Diabetes Care. 2026;49(Suppl 1):S261-S276. PubMed 41358886 (external site)
- 3.Mueller MJ, Sinacore DR, Hastings MK, Strube MJ, Johnson JE. Effect of Achilles tendon lengthening on neuropathic plantar ulcers: a randomized clinical trial. J Bone Joint Surg Am. 2003;85(8):1436-1445. PubMed 12925622 (external site)
- 4.Rinkel WD, Castro Cabezas M, van Neck JW, Birnie E, Hovius SER, Coert JH. Validity of the Tinel Sign and Prevalence of Tibial Nerve Entrapment at the Tarsal Tunnel in Both Diabetic and Nondiabetic Subjects: A Cross-Sectional Study. Plast Reconstr Surg. 2018;142(5):1258-1266. PubMed 30113445 (external site)
- 5.Sammarco GJ, Chang L. Outcome of surgical treatment of tarsal tunnel syndrome. Foot Ankle Int. 2003;24(2):125-31. PubMed 12627619 (external site)
- 6.National Institute of Diabetes and Digestive and Kidney Diseases. National Diabetes Month. Reviewed August 2024. niddk.nih.gov (external site)
- 7.International Diabetes Federation. About World Diabetes Day. worlddiabetesday.org (external site)
- 8.Crawford F, Cezard G, Chappell FM, et al. A systematic review and individual patient data meta-analysis of prognostic factors for foot ulceration in people with diabetes: the international research collaboration for the prediction of diabetic foot ulcerations (PODUS). Health Technol Assess. 2015;19(57):1-210. PubMed 26211920 (external site)
- 9.Kanji JN, Anglin RE, Hunt DL, Panju A. Does this patient with diabetes have large-fiber peripheral neuropathy? JAMA. 2010;303(15):1526-1532. PubMed 20407062 (external site)
- 10.Wang F, Zhang J, Yu J, et al. Diagnostic accuracy of monofilament tests for detecting diabetic peripheral neuropathy: a systematic review and meta-analysis. J Diabetes Res. 2017;2017:8787261. PubMed 29119118 (external site)
- 11.Dros J, Wewerinke A, Bindels PJ, van Weert HC. Accuracy of monofilament testing to diagnose peripheral neuropathy: a systematic review. Ann Fam Med. 2009;7(6):555-558. PubMed 19901316 (external site)
- 12.Scott JE, Hendry GJ, Locke J. Effectiveness of percutaneous flexor tenotomies for the management and prevention of recurrence of diabetic toe ulcers: a systematic review. J Foot Ankle Res. 2016;9:25. PubMed 27478505 (external site)
- 13.Bus SA, Sacco ICN, Monteiro-Soares M, et al. Guidelines on the prevention of foot ulcers in persons with diabetes (IWGDF 2023 update). Diabetes Metab Res Rev. 2024;40(3):e3651. PubMed 37302121 (external site)
- 14.Mauermann ML, Staff NP. Peripheral Neuropathy: A Review. JAMA. 2026;335(3):255-266. PubMed 41247746 (external site)
- 15.Callaghan BC, Price RS, Feldman EL. Distal symmetric polyneuropathy: a review. JAMA. 2015;314(20):2172-2181. PubMed 26599185 (external site)
- 16.Rinkel WD, Castro Cabezas M, Birnie E, Coert JH. The natural history of tarsal tunnel syndrome in diabetic subjects. J Plast Reconstr Aesthet Surg. 2020;73(8):1482-1489. PubMed 32276769 (external site)
This article is general health information and isn’t a substitute for advice from a clinician who knows your history. Read our medical disclaimer and how we review content.
More from the blog
Finding the cause
Weakness in legs and feet vs numbness: what your nerve symptoms mean
Numbness and weakness come from different nerve fibers, and the pattern points to the cause. A trapped nerve causing foot drop can often be fixed with surgery, while slowly spreading weakness without numbness needs a neurologist.
Finding the cause
How to describe nerve pain to your doctor
The words you use are real clues. What to say about burning, tingling and electric pain, and how to prepare for your visit.
Finding the cause
EMG and nerve conduction study: what to expect
What the tests measure, what they feel like, how to prepare, and why a normal result doesn’t always rule out a nerve problem.